What is chronic diarrhea, and how can it be distinguished from acute diarrhea?
Chronic diarrhea is defined as liquid or semi-liquid stools lasting longer than 4 weeks—a threshold that warrants a comprehensive medical evaluation. It is a telltale symptom of many digestive disorders, some of which are serious. Just as with acute diarrhea, rehydration remains a priority, but it is only a temporary measure in cases of chronic diarrhea.
- Acute diarrhea: < 14 days — often infectious (viral, bacterial, parasitic) — usually resolves on its own — see our page on acute diarrhea
- Chronic diarrhea: > 4 weeks — non-infectious in the vast majority of cases in France — a medical evaluation is essential before any treatment
- Red flags (urgent consultation): blood in the stool, unintentional weight loss > 5%, nighttime abdominal pain, prolonged fever, anemia — consider IBD, colorectal cancer, celiac disease
- Pathophysiological classification: secretory (hypersecretion) — osmotic (malabsorption) — motility-related (accelerated transit, IBS) — exudative (mucosal lesions, IBD)
- Epidemiology: 5% of the adult population—women are slightly more affected—significant impact on quality of life and occupational activity
What are the main causes, and how can they be identified?
- Celiac disease: gluten intolerance — chronic diarrhea + malabsorption + deficiencies (iron, B12, D) — diagnosis via anti-transglutaminase antibodies + duodenal biopsy — strict, lifelong gluten-free diet
- Chronic Inflammatory Bowel Diseases (IBD): ulcerative colitis (UC) and Crohn’s disease — diarrhea + blood + pain + fever — endoscopic and histological diagnosis — anti-TNF and anti-IL-12/23 biologics
- Irritable bowel syndrome (IBS): chronic diarrhea without organic lesions — Rome IV criteria — brain-gut axis — FODMAP diet + probiotics + stress management
- Lactose intolerance: osmotic diarrhea after consuming dairy products — elimination diet or hydrogen breath test
- Pancreatic malabsorption: exocrine pancreatic insufficiency (chronic pancreatitis) — floating, foul-smelling, fatty stools (steatorrhea) — pancreatic enzyme replacement therapy
Medical Evaluation and Treatment of Chronic Diarrhea
Chronic diarrhea always warrants a medical evaluation before starting treatment—self-treatment delays diagnosis and may mask a serious condition. Our line of probiotics provides complementary support once a diagnosis has been established.
- Initial workup: CBC + CRP (inflammation) — TSH (hyperthyroidism) — IgA anti-transglutaminase antibodies (celiac disease) — stool culture + parasitological examination — fecal calprotectin (IBD marker)
- Colonoscopy: essential for patients over 50 years of age, those with blood in the stool, weight loss, or a family history of colorectal cancer—routine biopsies for histology
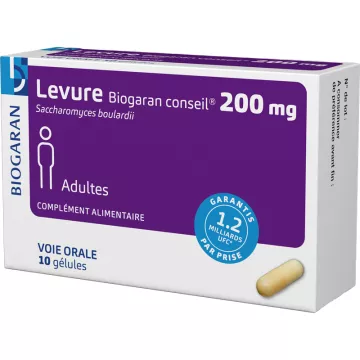
- Probiotics: Saccharomyces boulardii, Lactobacillus rhamnosus GG — effective for chronic post-antibiotic diarrhea and IBS — treatment duration of at least 4–8 weeks
- FODMAPs diet (fermentable oligosaccharides, disaccharides, monosaccharides, and polyols): reduction of fermentable carbohydrates — proven efficacy in IBS with a diarrhea-predominant pattern — dietary supervision recommended
- Biotherapies (IBD): anti-TNF (infliximab, adalimumab), anti-integrin (vedolizumab), anti-IL-12/23 (ustekinumab)—mucosal remission and reduced flare-ups—follow-up by a specialized gastroenterologist
Daily Management and Lifestyle
- Soluble fiber (psyllium, pectin): regulates stool consistency — improves bowel movements without accelerating them — increase intake gradually to avoid bloating — see our page on improving bowel movements
- Hydration: at least 1.5–2 L/day — water or vegetable broth — to compensate for chronic fluid loss
- Stress management: central brain-gut axis in IBS — cardiac coherence, mindfulness meditation, CBT — documented effect on stool frequency in IBS with a diarrhea component
- Foods to avoid during flare-ups: dairy products (if intolerant), fatty foods, sweeteners (sorbitol, xylitol), alcohol, coffee, spicy foods
- Regular medical follow-up: gastroenterology appointment every 6–12 months — treatment adjustment based on progress — monitoring fecal calprotectin levels for IBD