What is a patellar injury, and what are its main types?
A patellar injury encompasses several distinct conditions affecting the patella and its surrounding structures—each with its own specific cause and treatment. Our joint comfort line offers active ingredients tailored to recovery and prevention.
- Patellar chondropathy: wear and tear of the cartilage beneath the patella — pain beneath the patella when going down stairs or after prolonged sitting — stages 1 through 4, similar to osteoarthritis — see our osteoarthritis page
- Patellofemoral syndrome (PFS): Anterior knee pain caused by patellar misalignment—common among runners and cyclists—related to an imbalance between the vastus medialis and vastus lateralis muscles and the morphology of the trochlear groove
- Patellar tendinitis (jumper’s knee): inflammation of the patellar tendon (connecting the patella to the tibia) — pain at the tip of the patella during jumping and acceleration — see our page on tendinitis
- Patellar dislocation: lateral displacement of the patella out of the trochlear groove—urgent reduction + immobilization—MRI to assess associated cartilage damage
- Patellar fracture: direct trauma or violent quadriceps contraction — X-ray or CT scan required — surgical treatment if displaced
What supplements can support recovery from a patellar injury?
Patellar injuries often involve both a cartilaginous component and a tendinous-ligamentous component—the most effective supplements address both of these aspects. Find these formulas in our Joint Collagen and Sports Wellness lines.
- Glucosamine + chondroitin: structural support for patellar cartilage (chondropathy) and the tendinous-ligamentous matrix—1,500 mg glucosamine + 800–1,200 mg chondroitin per day
- Hydrolyzed marine collagen + vitamin C: promotes collagen synthesis in the patellar tendon and subpatellar cartilage — take 30–60 minutes before physical therapy
- Omega-3 (EPA/DHA): reduce tendinocartilaginous inflammation — particularly useful for patellar tendinitis and inflammatory patellofemoral syndrome
- Magnesium: reduces quadriceps spasms that increase femoropatellar pressure — 300–400 mg/day
- Oral hyaluronic acid: improves the viscosity of the femoropatellar synovial fluid — used as a complement to prescription intra-articular injections
Strengthening the vastus medialis and patellofemoral rehabilitation
The vastus medialis obliquus (VMO) is the key muscle for patellar stability—targeted strengthening of this muscle is the most effective conservative treatment for patellofemoral syndrome.
- VMO strengthening exercises: full-range squats (final third of extension), lateral step-ups, isometric extensions with slight flexion — prioritize closed-kinetic-chain exercises (less femoropatellar stress)
- Exercises to avoid: full-leg extensions on a Roman chair (maximum patellar pressure in the mid-range of motion) — leg press with flexion > 90° — deep squats during the painful phase
- Patellar taping: McConnell technique — a strapping band that repositions the patella medially — immediate reduction in pain during activities — useful for maintaining rehabilitation
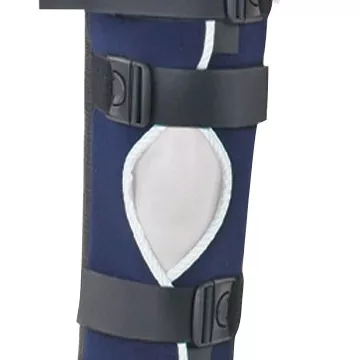
- Patellar knee brace: silicone ring around the patella — guides patellar gliding — useful for patellofemoral syndrome and patellar tendinitis — our sports support line
- Correction of biomechanical factors: orthotic insoles for hyperpronation, strengthening of hip stabilizers (abductors, external rotators)—the hip controls knee biomechanics
Patellar tendinitis (jumper’s knee): characteristics and treatment
- At-risk populations: volleyball players, basketball players, handball players, jumpers—repeated stress from explosive knee extension
- Clinical diagnosis: pain on palpation of the tip of the patella — single-leg squat test — MRI to assess tendon degeneration (tendinosis)
- Eccentric quadriceps strengthening: slow, controlled descent on an inclined plane — gold standard treatment for patellar tendinitis — a 12-week program is necessary for a lasting effect
- PRP and shockwave therapy: options for chronic cases resistant to eccentric strengthening — see our tendinitis page
- Return to sports if pain ≤ 3/10 during the single-leg squat + strength ≥ 90% on the unaffected side — no fixed time frame alone